Chapter 3 - Into the Surgical Suite
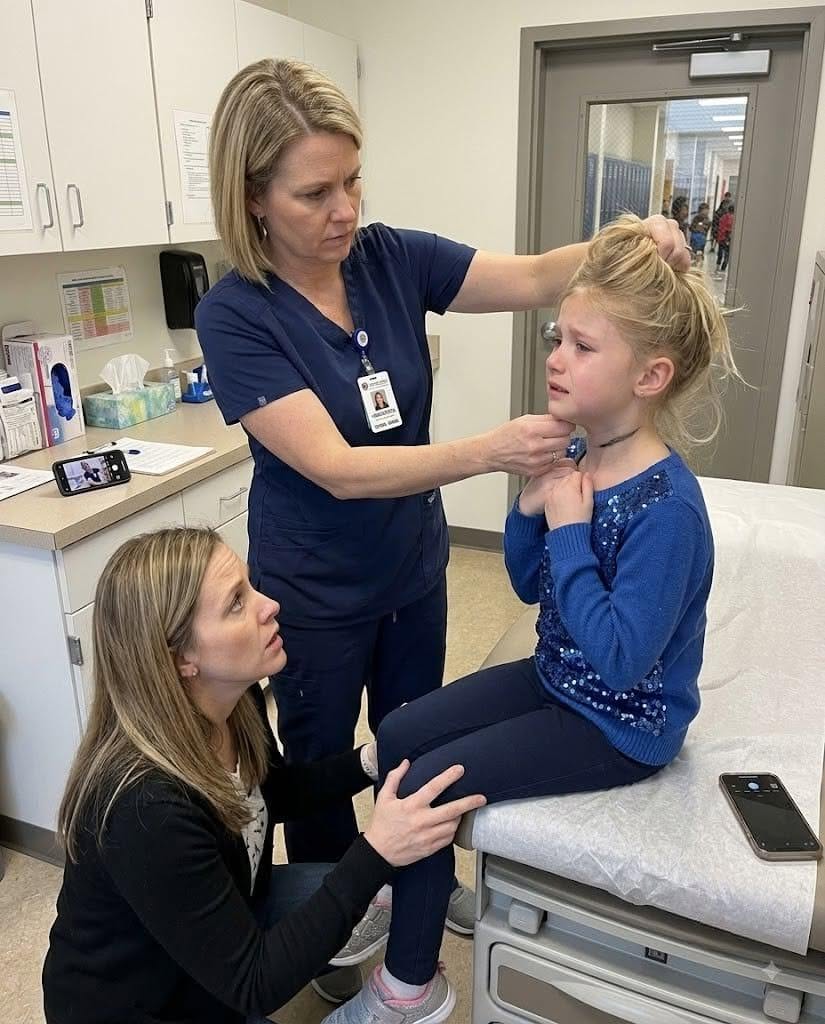
The waiting room of the pediatric surgical wing was lit by muted overhead lamps that seemed designed to keep anxiety at a low simmer, though it did little to ease the knot in my stomach. The clock on the wall read 3:42 PM. Every tick of the second hand sounded like a hammer striking an anvil.
I sat with my arms wrapped tightly around my middle. My husband, David, burst through the double doors twenty minutes later, his face pale and eyes wide with panic. His jacket was half-zipped, and he held his car keys so tightly his fingers were trembling.
"Where is she? Is she in surgery?" he asked, dropping into the vinyl chair beside me and pulling me into a desperate hug.
"They took her down ten minutes ago," I said, my voice breaking for the first time since this nightmare began. "David, it was a wire bristle. From your brother's grill brush."
David froze, his jaw slackening as the realization hit him. "Oh God... the brush I used to clean the grate before we cooked the chicken." He buried his face in his hands, a low groan escaping his chest. "I did this to her."
"No," I said firmly, taking his wrists and forcing him to look at me. "You didn't know. Nobody thinks a tiny wire on a grill brush is going to end up inside their daughter's neck. But we have to focus on her now."
We sat together in the quiet room, holding hands as the surgical clock ticked onward. Outside, twilight began to settle over the city, turning the tall glass windows of the hospital into dark gray mirrors.
Inside Surgical Suite 4, Dr. Evelyn Reyes, a pediatric head and neck surgeon, was leading the operation. Through the small glass window of the waiting area observation bay—which we were permitted to view from a distance alongside a patient liaison—we could see the intense focus of the surgical team.
Dr. Reyes operated with delicate precision. Because the wire was so tiny—roughly twelve millimeters long and less than a millimeter thick—finding it in the dense, fibrous layers of the anterior neck muscles was like hunting for a needle in a haystack.
"Fluoroscopy machine, please," Dr. Reyes instructed her team, her voice calm despite the high stakes.
A mobile X-ray unit was maneuvered over Chloe's neck while she lay under general anesthesia. The real-time imaging showed the exact position of the metallic foreign body. It had lodged near the sternocleidomastoid muscle, dangerously close to the carotid sheath.
"It's deeper than the initial ultrasound suggested," Dr. Reyes noted, studying the live monitor. "The tissue contraction from swallowing drove it further posterior. We need to make a careful transverse neck incision along the natural skin crease to minimize scarring and avoid damaging the marginal mandibular branch of the facial nerve."
With surgical scalpels, Dr. Reyes made a microscopic incision directly over the dark track on Chloe's skin. The dark line, as expected, was a sinus tract created by inflammatory tissue and localized subcutaneous bleeding where the metal had scraped against the muscle fibers.
Using micro-dissecting forceps, Dr. Reyes carefully navigated through the delicate layers of platysma muscle. The surgical team monitored Chloe’s vital signs continuously. Her heart rate remained stable, but every millimeter mattered; a slight slip could tear the surrounding vessel walls or nick the recurrent laryngeal nerve, which controlled her voice box.
"I have visual contact with the inflammatory capsule," Dr. Reyes announced after forty-five painstaking minutes. "Forceps."
She reached into the tiny incision, guiding the delicate instrument around the foreign structure. The room held its collective breath as Dr. Reyes gently clamped down on the hidden object. With slow, steady traction, she began to withdraw the metal fragment.
Out came a thin, silver-colored wire, coated in dark oxidized residue and micro-clots. It was slightly curved, precisely matching the bristle of a standard wire grill brush.
"Foreign body retrieved in its entirety," Dr. Reyes said, holding it up for the scrub nurse to place into a sterile sample container. "Check the tissue bed for secondary fragments or foreign debris."
Using high-resolution intraoperative ultrasound, the team scanned the area again. No other metal particles remained. The mucosal tear in her upper esophagus was small enough to heal spontaneously without requiring a complex flap repair, provided she remained on liquid nutrition and intravenous antibiotics for a few days.
"Irrigate the wound thoroughly with sterile saline," Dr. Reyes ordered. "Then we'll perform a multi-layer closure with absorbable sutures and apply a cosmetic skin adhesive to minimize external scar tissue."
Back in the waiting area, the door swung open at 5:15 PM. Dr. Reyes walked out, pulling down her surgical mask.
David and I stood up instantly, our heartbeats pounding in our ears.
"Mr. and Mrs. Mercer?" Dr. Reyes asked, a small, weary smile appearing on her lips. "Chloe is out of surgery. The operation was a complete success. We retrieved the wire fragment entirely without any damage to her nerves, voice box, or major blood vessels."
I collapsed against David's shoulder, letting out a sob of pure relief. "Thank you... thank you so much."
"She's resting comfortably in the PACU (Post-Anesthesia Care Unit)," Dr. Reyes continued. "She will need to stay in the hospital for two to three days for observation and intravenous antibiotic therapy to ensure no deep neck space infection develops. But overall, her prognosis is excellent. You caught this just in time."
May you like


"If we had waited another day..." David started, his voice choked.
"If she had continued to swallow solid food, that wire would likely have eroded into her carotid artery within twenty-four hours," Dr. Reyes said quietly. "You did the right thing by trusting your instincts and bringing her straight here."







